Percutaneous left atrial appendage occlusion
Percutaneous left atrial appendage occlusion closes the appendage with an implanted device in nonvalvular atrial fibrillation to reduce stroke risk from appendage thrombi. It is mainly used in selected patients with a major problem with long-term oral anticoagulation.
Percutaneous left atrial appendage occlusion isolates the appendage with a device in nonvalvular atrial fibrillation. It is used mainly when stroke risk is high and a nonreversible contraindication to long-term oral anticoagulation exists, or when major bleeding risk remains unacceptable after a full comparison. Oral anticoagulation generally has more extensive evidence, so inconvenience or a wish to stop medicines is not an automatic indication. Occlusion does not treat atrial-fibrillation symptoms and does not remove other stroke mechanisms. Individualized short-term antithrombotic treatment remains necessary after the procedure, and transesophageal echocardiography, or TEE, or CT assesses device position, residual leak, and device-related thrombus. Major risks include cardiac tamponade, stroke, vascular injury, device embolization, and death.
Quick Reference
Treatment
1 hours – 2 hours
Observation
0.9 months
Department
Cardiology
Who Is This For
Is Percutaneous left atrial appendage occlusion Right for You?
Good Candidates
- Nonvalvular atrial fibrillation with high stroke risk and a nonreversible contraindication to long-term oral anticoagulation.
- In some guidelines and regions, very high major-bleeding risk when the patient still prefers occlusion after understanding that oral anticoagulation has more extensive evidence.
- Feasible appendage anatomy confirmed by atrial-fibrillation, structural-heart, and imaging teams, with acceptance of short-term antithrombotic treatment and possible further intervention.
May Not Be Suitable
- No indication for anticoagulation, untreated appendage thrombus, unsuitable anatomy, active infection, or inability to complete perioperative antithrombotic treatment and imaging follow-up.
- A mechanical valve or moderate-to-severe mitral stenosis outside the routine device evidence for nonvalvular atrial fibrillation.
- Only inconvenience with medicine or a wish to stop it without a reasonable contraindication or high bleeding risk; a device must not be presumed safer by default.
Step-by-Step Process
How Percutaneous left atrial appendage occlusion Works
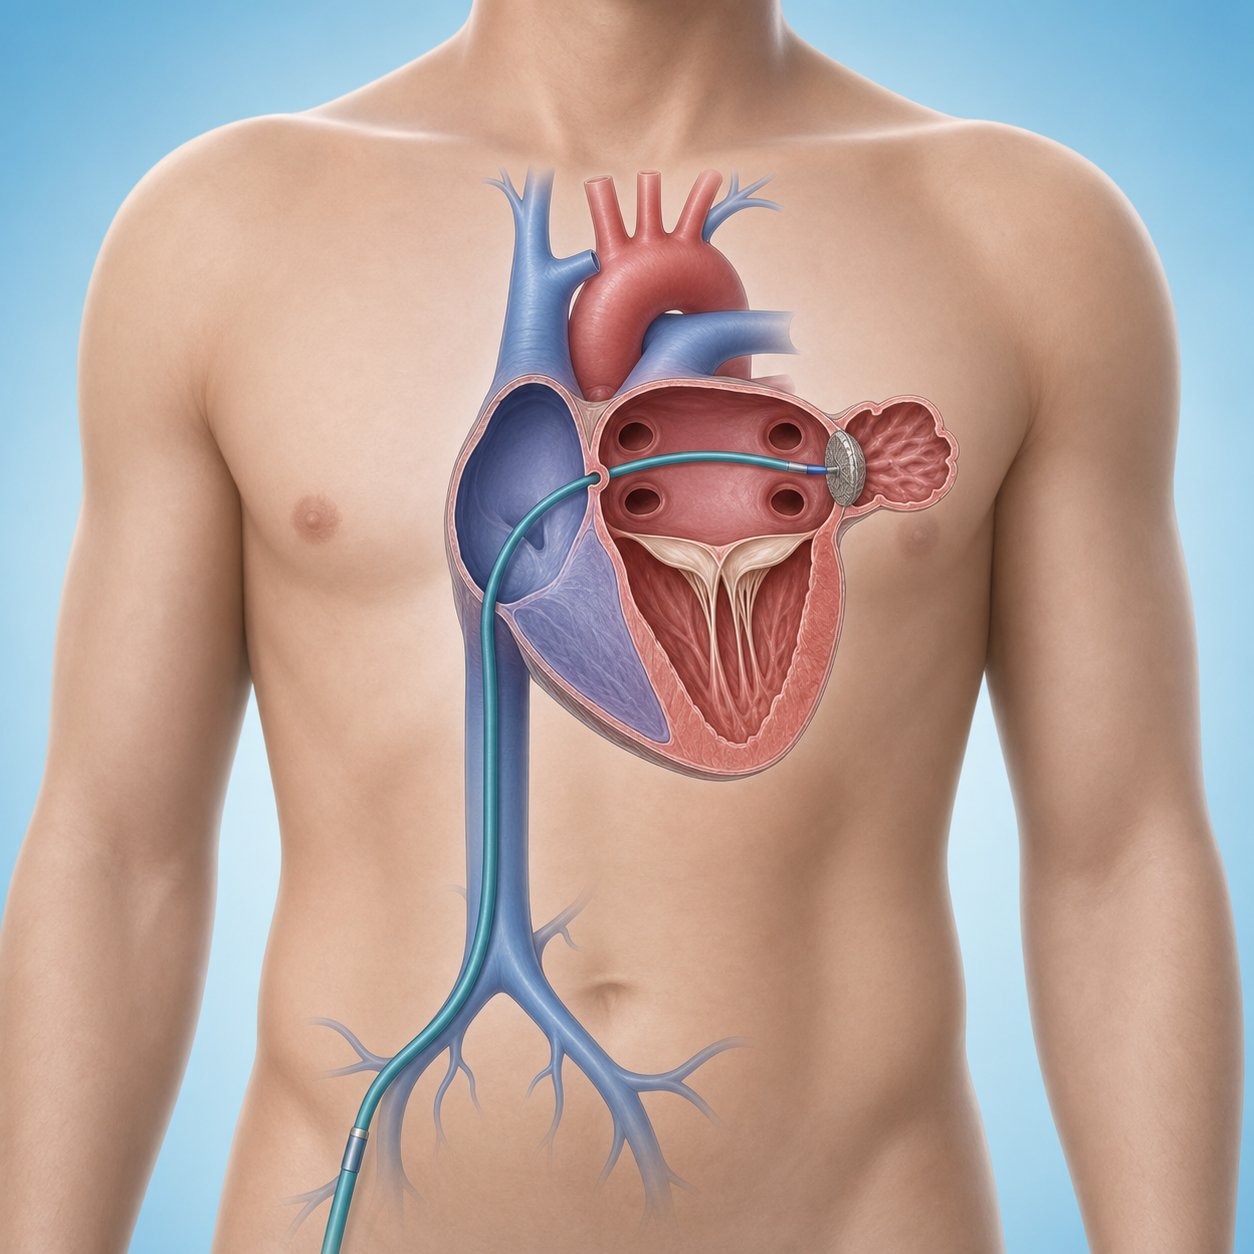
Confirm the need for an alternative to anticoagulation
Compare evidence, bleeding risk, and patient preference for continued or adjusted anticoagulation and occlusion and confirm that short-term antithrombotic treatment is possible.
Implant the occluder through the atrial septum
Enter the left atrium through the femoral vein, size and deploy the device under imaging guidance, and confirm position, stability, and residual leak.
Achieve hemostasis and give short-term antithrombotic treatment
Observe the access site, pericardial effusion, and neurologic status and begin a short-term anticoagulant or antiplatelet plan according to device and patient risk, with a bleeding plan.
Confirm by imaging and manage stroke risk long term
Use planned TEE or CT to assess device seal and thrombus and adjust antithrombotic treatment accordingly. Continue managing atrial-fibrillation symptoms and stroke risks not arising from the appendage.
A short admission is usual, but treatment continues through post-procedure antithrombotic therapy and required imaging. Device thrombus or a substantial residual leak can require extended or changed treatment.
Cost Information
Cost Estimate for Percutaneous left atrial appendage occlusion
What's Included
Costs are quoted in Chinese yuan (RMB). For full self-payment without Chinese medical insurance, request a quote for the selected appendage-occlusion device brand and size. Itemize preoperative CT or TEE, intraoperative TEE or intracardiac ultrasound, the device and delivery system, anesthesia, the ward and expected stay, and post-procedure antithrombotic medicines. Device replacement, complications, and prolonged admission are charged separately.
Before Your Visit
What to Prepare
Required Tests & Examinations
If you already have recent valid test results, bring the reports. If not, these assessments can usually be completed in China before the procedure.
Confirm atrial fibrillation, stroke risk, the long-term anticoagulation problem, and alternatives and have a structural-heart team assess net benefit.
Use TEE or CT to assess appendage anatomy and thrombus and check blood count, kidney function, coagulation, bleeding history, and anesthesia risk.
Identify the site and reversible causes of previous bleeding and compare the net benefits of adjusting a DOAC, treating the bleeding source, and occlusion.
Documents & Materials to Bring
Required to Bring
Electrocardiogram, echocardiography or CT, records of previous stroke or transient ischemic attack, and results assessing appendage anatomy and thrombus.
All medicines and allergies, blood count and kidney function, and names, doses, and adverse reactions of current and previous anticoagulants.
Endoscopy, imaging, admission, and transfusion records supporting a long-term contraindication or major bleeding risk, plus availability of post-procedure antithrombotics and arrangements for imaging follow-up.
Companion & Support
A responsible adult should accompany the patient for the procedure or discharge and early recovery; follow local transport, driving, and overnight-supervision rules.
After Treatment
Recovery & Follow-Up
The procedure does not immediately remove the need for all antithrombotic medicines. Complete the prescribed course and let the clinician adjust it after imaging.
Occlusion treats only thrombi arising from the appendage; it does not treat the atrial-fibrillation rhythm, every cause of stroke, or other cardiovascular risks.
Sudden speech difficulty, limb weakness, or visual disturbance after occlusion still requires an immediate stroke emergency response; the device does not exclude stroke.
Follow-Up Schedule
Complete TEE or CT within weeks to months according to the device and center pathway and continue reviewing stroke and bleeding. Chest pain or breathlessness, neurologic symptoms, syncope, or substantial bleeding requires emergency care.
Related Conditions
Conditions This Procedure Treats
Ready to Plan Percutaneous left atrial appendage occlusion in China?
Let Carevia help you find the right hospital, coordinate your treatment, and arrange every detail of your medical trip.
Frequently Asked Questions
Need personalized guidance?
Our care coordinators can help you assess whether this procedure fits your situation.
Contact Us