Four-pillar foundational medical therapy for HFrEF
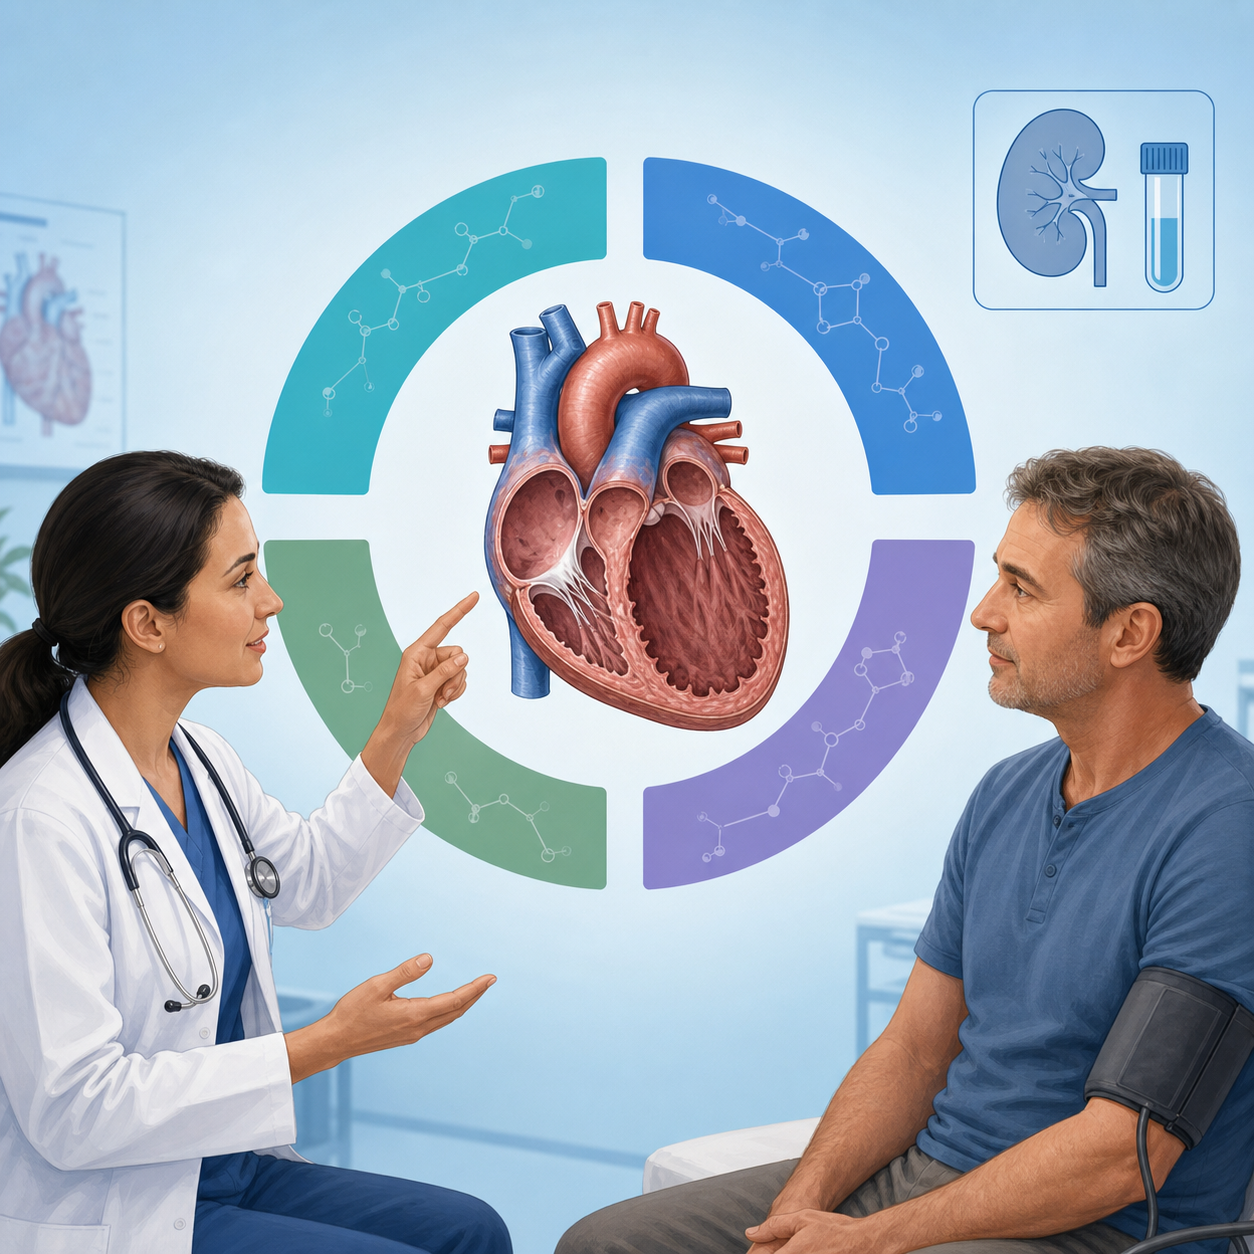
The four foundational pillars for HFrEF comprise one of ARNI, ACEI, or ARB, together with an evidence-based beta blocker, an MRA, and an SGLT2 inhibitor, aiming to reduce hospitalization and death within individual tolerability.
The foundational four-pillar treatment for heart failure with reduced ejection fraction, or HFrEF, generally comprises one of an angiotensin-receptor neprilysin inhibitor, or ARNI, an angiotensin-converting enzyme inhibitor, or ACEI, or an angiotensin II receptor blocker, or ARB, plus an evidence-based beta blocker, a mineralocorticoid-receptor antagonist, or MRA, and a sodium-glucose cotransporter 2 inhibitor, or SGLT2 inhibitor. The aims are lower mortality and heart-failure admissions and better symptoms. The four classes are not interchangeable, and fixed maximum doses need not be reached on the same day. According to blood pressure, heart rate, volume, kidney function, and potassium, a clinician establishes all tolerated classes early and titrates them in an overlapping sequence over weeks to months. A diuretic relieves fluid retention when congestion is present but is not one of the four prognosis-improving classes. Risks include hypotension, bradycardia, volume depletion, kidney-function changes, hyperkalemia, and drug-specific adverse effects.
Quick Reference
Observation
0 mins
Department
Cardiology
Who Is This For
Is Four-pillar foundational medical therapy for HFrEF Right for You?
Good Candidates
- Confirmed HFrEF without a class-specific contraindication and ability to monitor blood pressure, heart rate, kidney function, and electrolytes.
- Early establishment of all four tolerated classes after stabilization in hospital or outpatient care, without waiting for one class to reach its maximum dose before starting the next.
- A person able to attend frequent early reviews, record home weight, blood pressure, and heart rate, and complete kidney and electrolyte monitoring, while understanding the distinct role of each medicine.
May Not Be Suitable
- Cardiogenic shock, severe symptomatic hypotension, or marked hypoperfusion requires stabilization before the complete framework is started or increased.
- Acute kidney injury, severe hyperkalemia, or marked volume depletion requires holding relevant components, treating the trigger, and reassessing.
- Pregnancy or planned pregnancy excludes ARNI, ACEI, ARB, and MRA. A history of related angioedema or an inadequate safety interval after stopping ACEI before changing to ARNI also prevents immediate ARNI initiation.
- Do not start MRA when potassium or kidney function fails regional safety criteria or early potassium and kidney reviews cannot be completed.
- Active ketoacidosis, prolonged fasting, major surgery, or critical acute illness is not a setting to continue or start an SGLT2 inhibitor mechanically; pause and restart according to a clinician's plan.
Step-by-Step Process
How Four-pillar foundational medical therapy for HFrEF Works
Confirm congestion and the safety window
Assess volume, perfusion, blood pressure, heart rate, kidney function, and potassium and first treat acute decompensation and reversible triggers.
Establish all four classes early
The clinician selects one of ARNI, ACEI, or ARB and adds an evidence-based beta blocker, MRA, and SGLT2 inhibitor, without treating the classes as substitutes for one another.
Review safety early according to risk
After every start or increase, review symptoms, volume, blood pressure, heart rate, kidney function, and potassium according to the medicine and risk and address hypoperfusion, dehydration, bradycardia, or hyperkalemia first.
Titrate in parallel and reassess long term
At relatively short intervals, move toward individually tolerated doses, then continue treating the cause and reassess left-ventricular function and indications for device therapy after stabilization.
Treatment is generally long term. Do not stop it yourself even if ejection fraction improves. Reaching stable, appropriate doses may require several closely spaced visits.
Cost Information
Cost Estimate for Four-pillar foundational medical therapy for HFrEF
What's Included
Costs are quoted in Chinese yuan (RMB). For full self-payment without Chinese medical insurance, price each item in the actual 30-day prescription: one selected ARNI, ACEI, or ARB, an evidence-based beta blocker, an MRA, and an SGLT2 inhibitor, with each generic name, dose, manufacturer, and quantity. Itemize blood-pressure monitoring, kidney function, electrolytes, and follow-up separately. Titration and intolerance can change the regimen.
Before Your Visit
What to Prepare
Required Tests & Examinations
If you already have recent valid test results, bring the reports. If not, these assessments can usually be completed in China before the procedure.
Confirm the HFrEF diagnosis and LVEF and assess congestion, perfusion, blood pressure, heart rate, rhythm, and cause.
Check kidney function, sodium and potassium, blood count and iron, liver function, and all medicines, and record pregnancy possibility and previous angioedema.
Determine the cause and reversible contributors to reduced ejection fraction and assess parallel treatment needs for volume, iron deficiency, coronary disease, valve disease, and arrhythmia.
Documents & Materials to Bring
Required to Bring
Echocardiogram, electrocardiogram, and recent kidney function, electrolytes, blood count, iron studies, and other relevant test results.
Complete names and doses of medicines, allergies or adverse reactions, hospital records, and investigations of the cause.
Daily records of weight, blood pressure, heart rate, breathlessness, and edema and a written plan for temporary diuretic adjustment and when to seek care.
Companion & Support
A companion is usually unnecessary but can help with communication, mobility, or remembering instructions when needed.
After Treatment
Recovery & Follow-Up
Record weight and symptoms daily and follow the clinician's diuretic and emergency plan; do not stop several foundational medicines at the same time on your own.
Avoid NSAIDs, potassium-containing supplements, and medicines that may interact with heart-failure treatment unless assessed.
Rapid weight gain over several days, waking breathless at night, breathlessness at rest, syncope, or markedly reduced urine can signal decompensation or a drug problem and requires prompt contact according to the plan.
Follow-Up Schedule
After initiation or adjustment, repeat blood pressure, kidney function, and potassium within days to weeks according to risk, followed by continuing heart-failure care. Severe breathlessness at rest, syncope, hypoperfusion, or rapid fluid retention requires urgent treatment.
Related Conditions
Conditions This Procedure Treats
Ready to Plan Four-pillar foundational medical therapy for HFrEF in China?
Let Carevia help you find the right hospital, coordinate your treatment, and arrange every detail of your medical trip.
Frequently Asked Questions
Need personalized guidance?
Our care coordinators can help you assess whether this procedure fits your situation.
Contact Us